Sarah Hubbard
*About the Author: Sarah Hubbard
Sarah Hubbard is a medical writer for Certified Foot and Ankle Specialists with approximately 15 years of experience creating accurate, patient-focused healthcare content. She specializes in translating complex podiatric topics into clear, informative articles that help patients better understand foot and ankle conditions, treatment options, and preventive care.
That sharp, burning pain in your heel the moment your foot hits the floor in the morning is one of the most recognizable symptoms in podiatry. After a few steps it usually eases, which is why many people walk it off for weeks before coming in. In our Florida clinics, plantar fasciitis is one of the conditions we treat most often, but it’s also one of the most commonly misdiagnosed, both by patients and by providers who jump to conclusions based on the symptom alone.
The first thing we do when someone comes in with heel pain isn’t confirm plantar fasciitis. It’s rule out everything else. Here’s what we look at, what we find, and the treatment path we follow when the diagnosis holds.
What Is Plantar Fasciitis? (And What It Might Also Be)
The plantar fascia is a thick band of connective tissue that runs along the bottom of your foot, connecting your heel bone to the base of your toes. It absorbs shock and supports your arch with every step. When that tissue develops micro-tears from repetitive stress, it becomes inflamed, that’s plantar fasciitis.
The pain is usually sharpest first thing in the morning or after sitting for a long time, because the fascia shortens at rest and stretches back out when you stand. It tends to improve after a few minutes of walking, then return if you’re on your feet for extended periods. That pattern is worst at rest, better with movement, then worse again, It is the clinical hallmark.
What complicates the picture is that heel pain has several other causes that look similar and often get labeled plantar fasciitis incorrectly:
- Insertional Achilles tendinitis — pain and swelling at the back of the heel, not the bottom. Patients often feel a bony bump at the insertion point. Common in women who have worn high heels for years, and in people with tight calf muscles.
- Peripheral neuropathy — burning, tingling, or stabbing sensations that radiate from the toes toward the heel. Diabetes is a frequent underlying cause. Heel pain from neuropathy doesn’t follow the morning-first-step pattern.
- Fat pad atrophy — the cushioning tissue under the heel thins with age, causing a more diffuse, aching pain during weight-bearing rather than the sharp first-step pain of plantar fasciitis.
- Stress fracture of the calcaneus — a deep, aching pain that worsens consistently with activity. Common in runners who’ve increased mileage rapidly.
- Tarsal tunnel syndrome — compression of the posterior tibial nerve behind the ankle, which can cause shooting pain, numbness, or burning along the arch and heel.
- Bone tumors — rare, but persistent heel pain that doesn’t respond to any typical treatment warrants imaging to rule this out.
- Sever’s disease — In children and teenagers, heel pain is more often Sever’s disease, irritation of the growth plate at the back of the heel from repetitive stress — than plantar fasciitis, which is rare before adulthood. This guide focuses on adult plantar fasciitis; if your child or teenager has heel pain, that’s a different diagnosis and treatment path.
Getting the diagnosis right changes the treatment plan entirely. That’s why a clinical exam and, when indicated, imaging come first and not a printout of stretches.
What Does Plantar Fasciitis Feel Like?
The most specific symptom is pain with your first step out of bed in the morning, or after resting for more than 20 minutes. It’s typically a sharp, stabbing sensation at the base of the heel, sometimes extending into the arch. Most patients describe it easing within 10 to 15 minutes of walking, then returning later in the day after prolonged activity.
Pain that is constant throughout the day, that doesn’t ease with movement, or that spreads significantly beyond the heel suggests something other than classic plantar fasciitis and warrants a closer look.
Timing matters clinically. When symptoms have been present for fewer than six weeks, we consider it an acute presentation. Beyond that, it’s chronic, and the treatment sequence shifts. Chronic plantar fasciitis may involve degenerative changes in the fascia tissue rather than active inflammation, which changes which treatments are most effective.
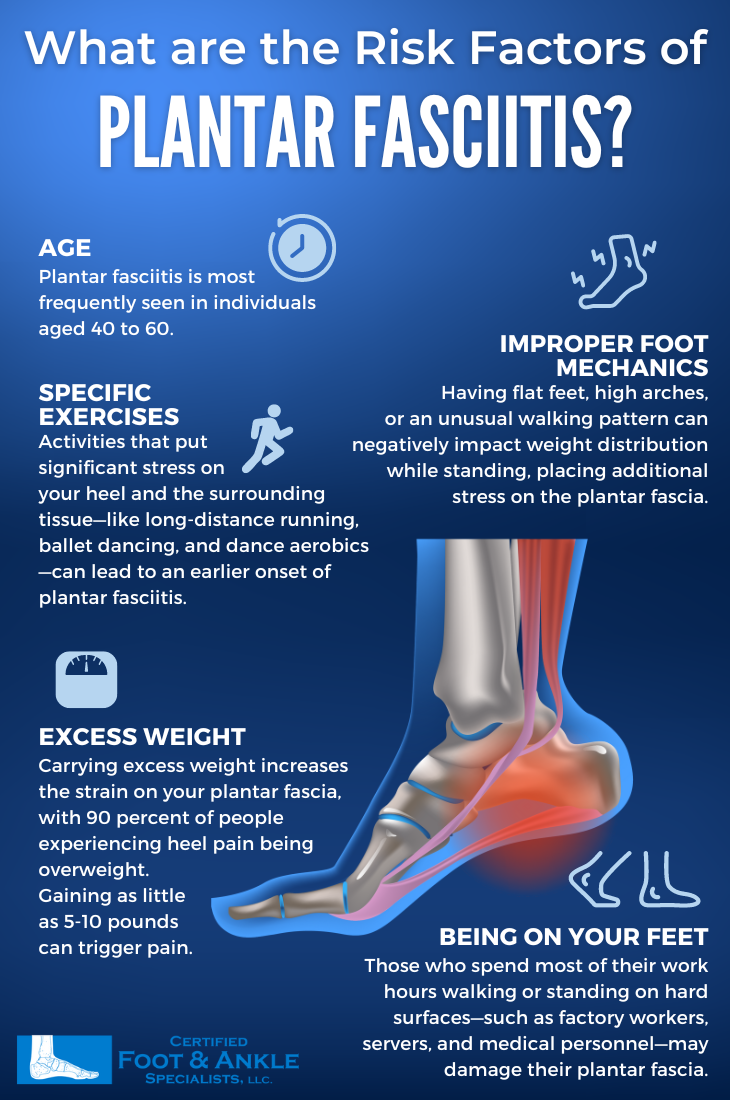
Who Gets Plantar Fasciitis? Risk Factors and Common Causes
Plantar fasciitis affects both athletes and non-athletes, and it develops from a combination of structural and lifestyle factors:
- Tight calf muscles and hyperpronation. These two are the most common biomechanical drivers we identify on exam. Inflexible calves limit ankle range of motion, forcing the plantar fascia to compensate. With hyperpronation, where the arch collapses inward during weight-bearing, the fascia is under continuous tension with every step, leading to micro-tears and inflammation.
- Foot structure. Both flat feet and high arches alter how force distributes across the foot, increasing stress on the fascia with different mechanisms.
- Age. Peak incidence is in adults between 40 and 60.1
- Activity changes. A sudden increase in running mileage, beginning a new exercise program, or transitioning to a job requiring prolonged standing are consistent triggers.
- Footwear. Shoes without adequate arch support or heel cushioning place more impact stress on the fascia.
- Body weight. Excess body weight increases the mechanical load the fascia absorbs with every step, which raises both the risk of developing plantar fasciitis and the difficulty of resolving it without addressing the underlying load.
In Florida, we see a specific pattern that doesn’t show up the same way elsewhere: patients who wear sandals, flip-flops, or unsupportive flat shoes for most of the year. Which is almost everyone here in south florida. Residents of florida have significantly less arch support than patients in climates that require structured footwear. Walking on hard tile, concrete, and pool decks with flat-soled shoes puts the plantar fascia under near-constant low-level strain. This shows up disproportionately in our retiree patients who are highly active on walking paths, golf courses, and pickleball courts in footwear designed for appearance rather than biomechanics.
How To Tell What's Causing Your Heel Pain
The location and timing of your heel pain provides important diagnostic clues. Use this quick-reference guide to understand what your symptoms may indicate before your appointment.
Pain Location |
When It Hurts Most |
Likely Condition |
|---|---|---|
| Bottom of heel | First steps in morning | Plantar fasciitis |
| Back of heel / lower calf | During or after running | Achilles tendonitis |
| Bottom of heel | Throughout the day with walking | Heel spur |
| Around the ankle / heel | Burning or tingling sensation | Nerve entrapment |
| Deep inside heel | With impact or direct pressure | Stress fracture |
| Heel in children 8–15 | During or after sports | Sever’s disease |
Could Your Heel Pain Be From Diabetes, Not Plantar Fasciitis?
Diabetes is one of the more common causes of heel pain that gets mistaken for plantar fasciitis. Diabetic peripheral neuropathy causes burning, tingling, or numbness that can center in the heel, but it typically doesn’t follow the sharp, first-step-in-the-morning pattern that defines plantar fasciitis. If you have diabetes and are experiencing heel pain, the distinction matters clinically — neuropathic pain and fascia inflammation are treated differently, and diabetic patients face added risk factors for both.
How We Diagnose Heel Pain at CFAS
The visit starts with a detailed history: when the pain began, what makes it better or worse, what you’ve already tried, your activity level, and what kind of footwear you typically wear. We’ll palpate the heel to identify the exact location of tenderness and assess your foot structure, arch height, calf flexibility, and gait.
Most patients get a weight-bearing X-ray during the same visit. X-rays don’t show the plantar fascia directly, but they rule out stress fractures and identify heel spurs. A heel spur is a calcium deposit that forms at the fascia’s attachment point on the heel bone, and it shows up on X-ray in many plantar fasciitis patients, but the spur itself is rarely the source of pain. The inflammation in the surrounding tissue is what hurts, and treating the fasciitis addresses it without needing to remove the spur surgically.
When the diagnosis is unclear after the clinical exam and X-ray or when symptoms are severe, and we need to quantify the degree of injury we’ll order a diagnostic ultrasound. Ultrasound shows the thickness and integrity of the plantar fascia in real time, which guides how aggressively we treat.
You’ll leave the first appointment with a confirmed diagnosis (or a plan to get one), a treatment protocol, and the first-line care items in hand.
The Treatment Path at CFAS: Conservative First
Conservative, non-surgical treatment resolves the majority of plantar fasciitis cases, and it’s always where we start.2 The goal in the first stage is to reduce inflammation and correct the biomechanical factors that caused it.
Here’s what the initial care plan looks like:
Anti-inflammatory management. We typically recommend an OTC NSAID (ibuprofen or naproxen) taken on a consistent schedule rather than only when pain spikes, because inflammation is ongoing even when discomfort fluctuates. A topical anti-inflammatory gel applied directly to the heel can provide additional targeted relief with fewer systemic effects.
Icing. Applying ice wrapped in a cloth for 15–20 minutes, up to three times a day, controls acute inflammation and is a useful add-on during flare-ups, particularly after activity or at the end of the day.
Stretching. Calf stretches and plantar fascia stretches are consistently among the most effective non-invasive treatments for this condition. They work because they address the underlying tightness and reduced range of motion that drives the problem. Form matters — doing the towel-pull stretch with improper technique can actually worsen symptoms. We have a detailed stretching guide written by our physicians.
Orthotics. Depending on your foot structure and gait, we may recommend a well-fitting OTC arch support that can be fitted at the visit, or cast for custom orthotics. Custom orthotics aren’t always necessary for many patients, an OTC insert addresses the biomechanics adequately. For flat feet, high arches, or significant hyperpronation, a custom device is usually the stronger long-term investment.
Footwear guidance. Avoiding barefoot walking, particularly on hard floors, is important during recovery. The foot needs arch support and cushioning throughout the day. We give specific guidance on what to look for and what to avoid, including a clear answer on which sandal types are acceptable options for patients who need open-toe footwear during recovery.
Night splints. For patients with severe morning first-step pain, a dorsiflexion night splint keeps the plantar fascia gently stretched during sleep, which significantly reduces the severity of that first-step pain. Not every patient needs one, but for those with pronounced morning symptoms, it makes a meaningful difference.
When Conservative Treatment Isn’t Enough
If pain doesn’t improve meaningfully after several weeks of consistent conservative care, or if it’s severe enough to significantly limit daily function, we move to the next level. ‘Consistent’ is the operative word: the treatments above work when followed every day, and patients who treat symptoms intermittently tend to plateau rather than progress.
Corticosteroid injections can reduce inflammation quickly and are useful for managing pain that’s preventing someone from being able to do the stretching and activity that drives recovery. The key limitation is that they’re not a standalone solution, the biomechanical issue that caused the inflammation still has to be addressed. We also limit the number of injections per site because repeated cortisone injections into the plantar fascia can weaken the tissue over time.2 For patients who haven’t responded to cortisone, or who have chronic, recalcitrant cases, we also offer platelet-rich plasma (PRP), stem cell, and amniotic fluid injections each targeting tissue regeneration rather than just inflammation control. Which option makes sense depends on how long you’ve had symptoms and how the tissue has responded to prior treatment.
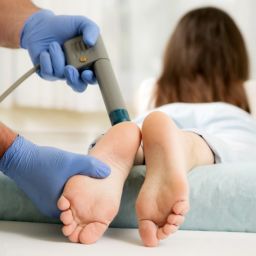
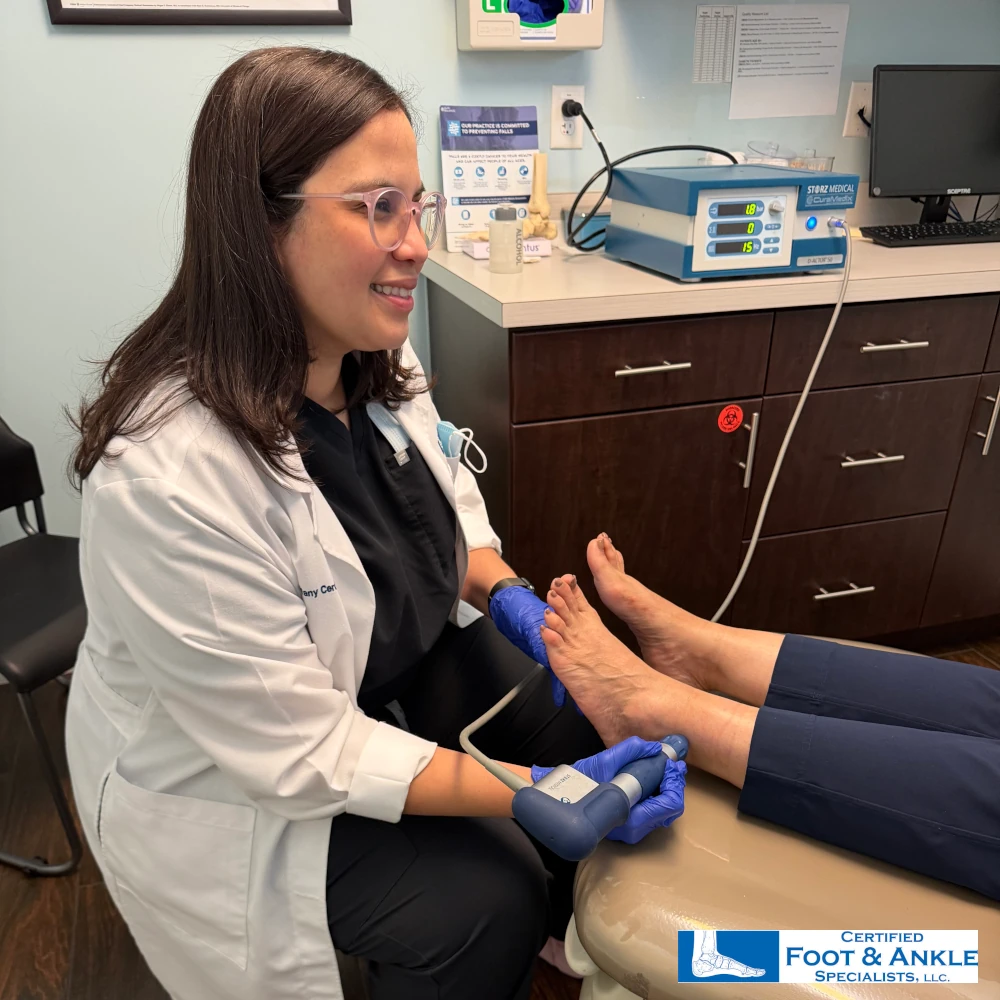
EPAT (Extracorporeal Pulse Activation Therapy), also called shockwave therapy, is a non-invasive, in-office procedure that uses high-energy acoustic pulses to stimulate tissue healing in the plantar fascia. It’s FDA-cleared and typically completed in a series of sessions, each lasting under 20 minutes, with no anesthesia required. For patients who haven’t responded to conservative treatment, EPAT produces strong outcomes and is often the difference between resolution and a surgical conversation.
Surgery (plantar fasciotomy) is a last resort, considered only after a patient has followed through on all conservative and interventional options for a minimum of six months with inadequate relief. It’s minimally invasive in most cases, and outcomes are generally good, but recovery involves a commitment to physical therapy and temporary activity modification. The large majority of patients never need to reach this stage. Fewer than 10% of plantar fasciitis patients ultimately need surgery.2
How Long Does Recovery Take? Honest Numbers.
Longer than most people want to hear, and shorter than they fear if they’re consistent.
Plantar fasciitis is a condition of connective tissue, and connective tissue heals slowly. Most patients with an acute presentation see meaningful improvement within three to six months of consistent conservative care. The majority are substantially better within ten months.1 What ‘consistent’ actually means: daily stretching, supportive footwear every day (not just sometimes), orthotics as directed, and limiting barefoot time.
EPAT shortens the timeline for many patients and is often recommended for those who need a faster recovery. Someone in a physically demanding job, training for an event, or whose symptoms have plateaued despite doing everything right.
For patients with chronic plantar fasciitis, symptoms lasting a year or more, the tissue may have undergone degenerative changes (sometimes called plantar fasciosis) rather than active inflammation. Degenerative changes don’t respond as well to anti-inflammatory treatment because at that stage, the primary issue is tissue breakdown rather than inflammation. Treatment at this stage shifts toward regeneration approaches including EPAT and, in some cases, platelet-rich plasma (PRP) therapy.
Recurrence is possible, particularly for patients who return to the same footwear habits and activity patterns that caused the problem. Part of what we work on before discharge is identifying and addressing those factors.
When Should You See a Podiatrist for Heel Pain?
If you’ve had heel pain for more than two weeks and it isn’t improving with rest and OTC care, it’s time to come in. Patients who seek evaluation early tend to have better outcomes and shorter recovery times than those who wait months. Partly because the tissue hasn’t had as long to develop compensatory patterns, and partly because the calf tightness that drives the problem is addressed before it becomes entrenched.
Come in sooner if you have any of these:
- Heel pain after an injury, fall, or sudden impact (rule out fracture)
- Significant swelling, warmth, or redness around the heel
- Pain severe enough to prevent normal weight-bearing
- Numbness, tingling, or burning extending up the leg
- No improvement after two weeks of consistent self-care
Our podiatrists at Boca Raton, Boynton Beach, and Coral Springs can typically assess and image a new heel pain case in one visit, with same-week appointments available for acute pain. Patients on Florida’s West Coast can reach our Tampa and Palm Harbor teams directly. If you’re not sure which location is closest, our appointment page lists all 14 clinics with direct scheduling.
Sources
1. American Orthopaedic Foot and Ankle Society (AOFAS). “Plantar Fasciitis.” aofas.org
2. American College of Foot and Ankle Surgeons (ACFAS). “Heel Pain (Plantar Fasciitis).” acfas.org
3. American Podiatric Medical Association (APMA). “Heel Pain.” apma.org
4. Mayo Clinic. “Plantar Fasciitis: Symptoms and Causes.” mayoclinic.org
Frequently Asked Questions About Plantar Fasciitis
Q: Does plantar fasciitis go away on its own?
A: It can ease on its own, but waiting rarely speeds recovery. Without addressing the underlying factors such as calf tightness, unsupportive footwear, and gait mechanics, the plantar fascia stays under the same stress that caused the problem. Many patients report partial improvement followed by recurrence once activity increases again. Structured treatment shortens the recovery window and significantly reduces the chance of it returning
Q: What’s the difference between plantar fasciitis and a heel spur?
A: A heel spur is a calcium deposit that develops at the point where the plantar fascia attaches to the heel bone, often as a response to chronic tension in the fascia. About half of plantar fasciitis patients have heel spurs visible on X-ray, but the spur itself isn’t usually what hurts. The inflammation in the surrounding tissue is the source of pain. Treating the plantar fasciitis typically resolves the heel pain; surgically removing the spur is rarely necessary.
Q: Are Birkenstocks good for plantar fasciitis?
A: Supportive sandals with a contoured footbed, Birkenstocks being the most common example, offer more arch support than a flat flip-flop and are preferable to going barefoot during recovery. They aren’t a medical orthotic and don’t correct biomechanics for every foot type, but for patients who need an open-toe option during Florida’s warmer months, a sandal with meaningful arch support is a reasonable choice. If you’re unsure whether a specific sandal is appropriate for your foot structure, ask us before buying.
Q: Can plantar fasciitis cause ankle pain?
A: Not directly, but the two are often linked. When heel pain causes someone to adjust their gait to avoid discomfort, the altered mechanics can load the ankle joints and Achilles tendon unevenly, sometimes producing secondary ankle pain or Achilles soreness. Addressing the plantar fasciitis typically resolves the secondary ankle symptoms as the gait normalizes.
Q: Can I run with plantar fasciitis?
A: The answer depends on the severity and stage of your symptoms. We’ve written a detailed guide specifically for runners and active patients — including how to modify training, what to monitor, and when to stop.
Q: Does plantar fasciitis ever fully resolve?
A: Yes, it can be, though it’s not caused by the same mechanism as plantar fasciitis. Diabetic peripheral neuropathy commonly presents as heel or foot pain, along with burning, tingling, or numbness. It doesn’t follow plantar fasciitis’s sharp first-step pattern. If you have diabetes and develop new heel pain, it’s worth having it evaluated specifically for neuropathy rather than assuming plantar fasciitis.
Q: Can heel pain be a sign of diabetes?
A: Yes, in most patients. The goal of treatment is complete resolution, not indefinite pain management. Patients who complete a full treatment course consisting of stretching, orthotics, footwear changes, and appropriate activity modification typically return to their prior activity level without ongoing symptoms. Some patients have recurrence if they return to the habits that caused the problem. Part of what we work on before discharge is identifying which factors to sustain long-term.
Q: Is heel pain ever a sign of cancer?
A: Very rarely. The overwhelming majority of heel pain comes from mechanical causes like plantar fasciitis, Achilles tendinitis, or nerve compression — not tumors. Bone tumors of the heel are uncommon. What sets a concerning presentation apart from ordinary heel pain is the pattern: pain that doesn’t ease with rest, pain that wakes you at night, swelling with no clear mechanical cause, or pain accompanied by unexplained weight loss. If your heel pain fits the usual pattern of getting worse with the first step, better with movement, and tied to activity. Then that’s a strong sign it’s mechanical, not something more serious. If it doesn’t fit that pattern, or if you’re worried, get it examined. Imaging can rule out rarer causes quickly.